Part Two
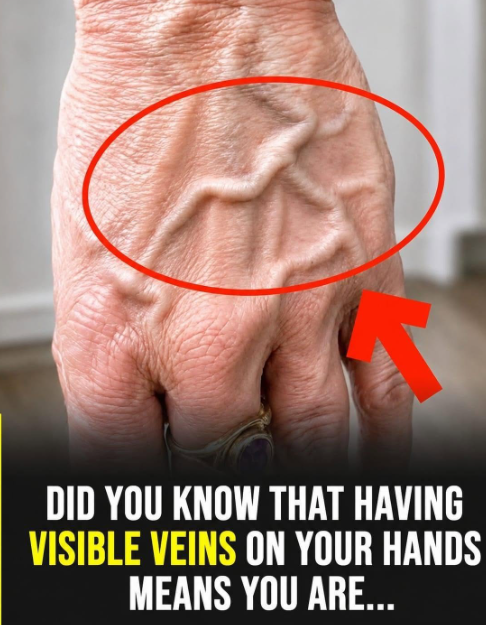
Anatomically, the dorsal venous network of the hand sits superficial to the deep fascial layer.
The primary driver of age-related vein prominence is the gradual loss of subcutaneous adipose tissue.
Dermal thinning reduces the structural cushion that once masked the underlying branching vascular tree.
Collagen and elastin degradation compromise skin elasticity, allowing slack tissue to drape over vessels.
Low body fat percentage strips away internal padding, making vascular maps sharply distinct regardless of chronological age.
Environmental temperature triggers vasodilation or vasoconstriction, altering superficial vessel volume dynamically throughout the day.
Physical exertion increases cardiac output and systemic blood pressure, temporarily swelling dorsal hand veins during active use.
Chronic sun exposure accelerates photoaging, breaking down structural extracellular matrix proteins in the hand dorsum.
Hydration status changes blood plasma volume, subtly accentuating or softening surface contour visibility.
Distinguishing physiological prominence from pathological distension requires evaluating symmetry, pain, and associated localized findings.
Superficial phlebitis or localized clotting can present with tenderness, warmth, and cord-like hardening along a segment.
Gravity pooling occurs when arms remain dependent for extended periods, temporarily increasing local hydrostatic pressure in superficial veins.
Hormonal fluctuations during aging alter vascular tone and fluid retention patterns across distal extremities.
Occupational or repetitive grip stress can hypertrophy regional blood flow dynamics and vessel wall resilience over time.
Dermatologic assessments use skin turgor and thickness metrics to differentiate normal senescence from cachexia or nutritional deficits.
Nutritional status, including amino acid and micronutrient sufficiency, dictates ongoing dermal matrix maintenance and repair capacity.
Cosmetic dermatology offers targeted interventions like dermal fillers, fat grafting, or laser remodeling to restore lost dorsal hand volume.
Prevention of premature dorsal hand aging centers on broad-spectrum ultraviolet shielding and aggressive epidermal barrier preservation.
Monitoring baseline changes over months provides far more clinical insight than isolated visual panic under harsh lighting.
Concluding summary: Visible hand veins represent a natural convergence of tissue thinning, adipose loss, thermal adaptation, and hydrodynamic reality; understanding the map transforms anxiety into appreciation for biological longevity.